

Short for: Hairline Restoration
Surgery: Doctor-led
Time Taken: 6-9 hours
Price: £3,500 – £5,500
Finance available






Short for: Hairline Restoration
Surgery: Doctor-led
Time Taken: 6-9 hours
Price: £3,500 – £5,500
Finance available

Every procedure at our Glasgow clinic is performed by a doctor on the GMC register
Our clinic is in the heart of Glasgow, a short walk from Buchanan Street subway and Queen Street station
Your surgeon is fully dedicated to your procedure from start to finish
Honest assessment of your donor hair and realistic outcome, no hard sell
The hairline is the first thing most people notice. It frames the face, shapes how you photograph, and when it recedes, it tends to be the change that finally prompts a consultation. At Hair Transplant Glasgow, hairline restoration is one of the most common procedures we perform, and in some ways the most technically demanding. The front edge has to look right from every angle, in every lighting condition, and it has to keep looking right as you age.
This page covers how we assess and plan hairline procedures, which techniques we use and why, what recovery looks like, and what the surgery costs. If you have questions this doesn’t answer, the free consultation is the right place to ask them.
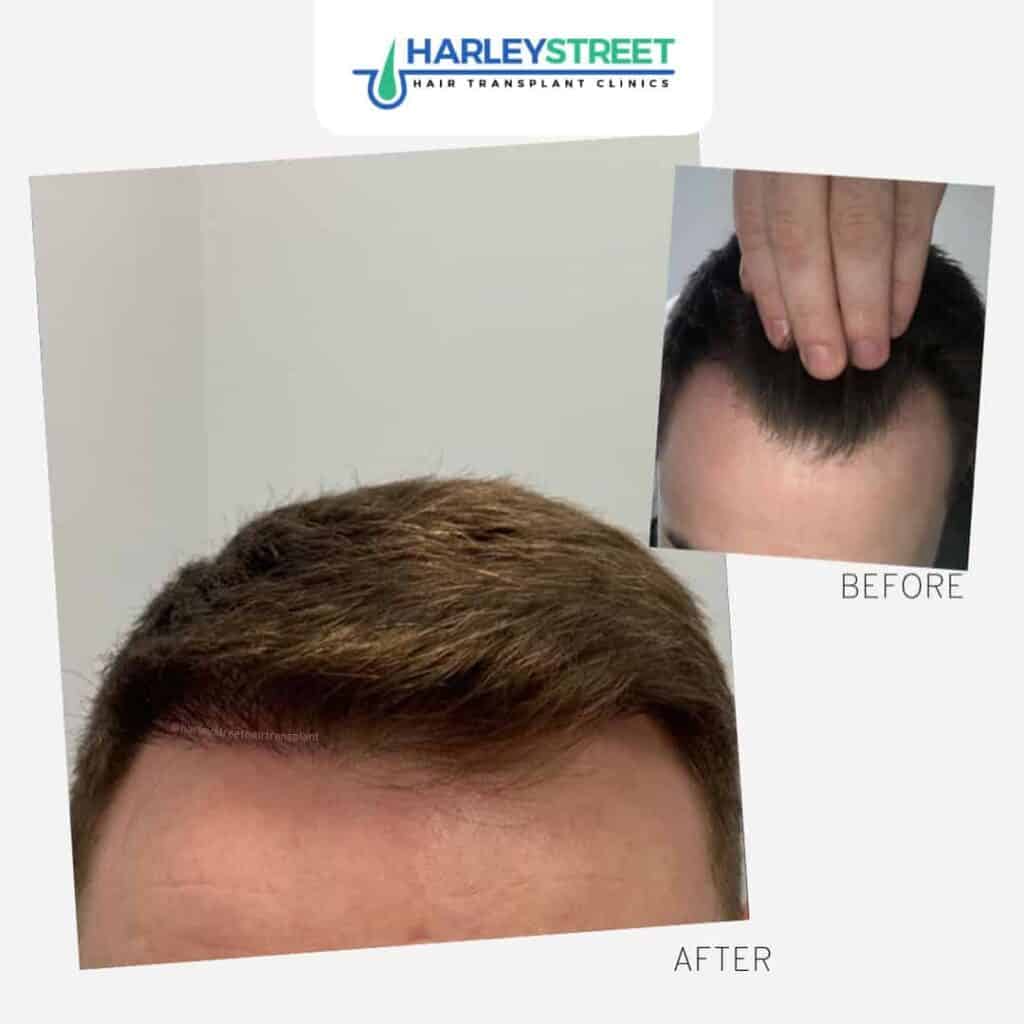
A selection of results from patients treated at our Glasgow clinic. All procedures were performed by our GMC-registered surgeons.

Hair Transplant Glasgow is on Buchanan Street in the city centre, accessible to patients from across Scotland. Edinburgh, Aberdeen, Dundee, Inverness: all within reasonable reach of the clinic, and all represented regularly in our consultation room. Hairline procedures are performed by Dr Aziz Elgindi or Dr Mohammed Ditta, both of whom have carried out thousands of procedures across the scalp, hairline, beard, and eyebrow areas.
Hairline surgery is not a straightforward fill-in job. The design has to work at 25 and still look appropriate at 55. That requires honest planning around where your hair loss is heading, not just where it is today. Younger patients particularly need that conversation before any grafts are placed.
Every hairline procedure starts with a detailed assessment. The surgeon examines your current pattern on the Norwood-Hamilton scale: NW2 and NW3 are the most common grades for hairline procedures, though higher classifications do come in and typically require a staged approach that addresses the hairline first and the crown separately.
Donor density matters as much as the recipient area. If your Norwood grade is high but your donor supply is limited, transplanting too aggressively early on depletes the resource you’ll need for future sessions. Honest planning means accounting for that from the start, not discovering it two years later.
Age and loss trajectory factor into every hairline conversation. For patients under 30 with active or unpredictable loss, we design a mature hairline rather than restoring a teenage one. A hairline positioned too low, or too dense at the front, will look mismatched in a decade if recession continues behind it. Hair characteristics also shape the plan: curl pattern, calibre, and the contrast between hair and scalp colour all affect how many grafts are needed to achieve the density you’re after.
An artificial-looking hairline is immediately obvious, and the cause is almost always the same: a straight edge, too much density at the front, or a position that doesn’t suit the face. Natural hairlines have irregularity built in. The leading edge is made up of single follicle grafts, fine one-hair units, that give way to two and three-hair grafts behind them. This transition zone is what creates the soft edge a real hairline has.
The front line itself is never straight. Small deviations, slight recession at the temples, minor asymmetry: these are the details that separate a result that looks grown from one that looks placed. Temporal points are part of the design, not an afterthought. The temples frame the lower face and contribute significantly to how the overall result reads.
Dr Elgindi draws the proposed hairline before surgery and discusses it with the patient in full. No grafts are placed until the design is agreed.
For most patients presenting at NW2 or NW3 with good donor density and a stable loss pattern, a single session of 1,500 to 2,500 grafts restores the hairline comprehensively. That’s the most common scenario we see.
Where it becomes more involved is patients at NW4 or above, or anyone with significant crown thinning alongside the hairline recession. In those cases we plan in stages: the hairline first, the crown or mid-scalp in a separate session. This isn’t a workaround; it’s the right approach. Doing both areas at once in a single session would require a graft count that could compromise donor density, and the results would be thinner in both areas than if each had been given its own session.
Finasteride is worth discussing as part of this planning conversation. For patients where loss is still actively progressing, medical treatment alongside surgery gives the most stable long-term result. Without it, native hair behind the transplanted hairline can continue to thin, potentially creating a patchy appearance over time that requires further surgical planning.
FUE is the method used in the majority of hairline procedures. Individual follicular units are extracted from the donor area with a micro-punch tool and implanted into the recipient sites. No linear scar, short recovery, and it allows precise control over graft selection. Most patients are past the visible redness and scabbing stage within 7 to 10 days.
DHI uses the Choi Implanter Pen to place grafts directly into the scalp without pre-made incisions, which gives additional control over the angle and depth of placement. In the hairline area, where the angle of emergence has a significant effect on how natural the result looks, this level of precision matters. It also reduces the time grafts spend outside the body, which can improve survival rates when packing density is high.
FUT comes into the picture when a patient needs a high graft count in a single session, or when they would rather not shave the donor area. It involves harvesting a strip from the back of the scalp, which leaves a linear scar but can yield more grafts in one sitting than FUE alone. For hairline-only procedures FUE or DHI is typically the better fit; FUT is more relevant in larger-scale restorations or for patients, including some women and transgender patients, who prefer to avoid shaving.
The technique recommendation is made at consultation based on your specific graft requirements, donor characteristics, and preference.
The transplanted hairs shed in the first two to four weeks. This is expected and does not indicate a problem: the follicle roots remain below the skin and begin producing new growth from around three to four months. Most patients see meaningful density from month six, with the full result, including complete maturation of the transplanted follicles, assessed at twelve months.
Days 1 to 3: mild swelling, redness, and small scabs at each recipient site. Normal daily activity can usually resume within 24 to 48 hours.
Weeks 1 to 2: scabbing resolves. Transplanted hairs begin to shed.
Months 1 to 3: the shedding phase. Little visible change. This is the period that requires the most patience.
Months 3 to 6: new hairs emerge. Texture is initially fine before thickening.
Months 6 to 12: progressive improvement in density. The hairline takes shape.
Month 12 onwards: final result. A review appointment is available at this stage.
Full aftercare guidance is in the post-procedure and aftercare section.
Cost is determined by graft count, which is confirmed at consultation once the surgeon has assessed your hairline and donor area. Hairline procedures typically fall between 1,000 and 2,500 grafts, though individual cases vary.
FUT or DHI carries an additional £1,000. All costs are confirmed with our patient advisor after your consultation. For a full breakdown and finance options, see the hair transplant cost page or enquire about hair transplant finance.
Most men with male pattern baldness at a stable or manageable stage are suitable. Good donor density, a loss pattern that has either levelled off or is being managed with medication, and realistic expectations about what surgery can achieve are the main factors. General health needs to allow for local anaesthetic.
Women experiencing hairline recession are also candidates, most commonly those with a naturally high hairline wanting to bring it down, or traction alopecia at the temples from years of tight styling. Female hairline procedures typically sit at 2,000 to 2,300 grafts and focus on restoring the rounded, feminine frame of the face. FUT is often the preferred method for women as it avoids shaving the donor area.
If you come in and the timing isn’t right, because loss is still progressing quickly or donor density isn’t sufficient yet, the surgeon will tell you directly. We’d rather recommend a review in twelve months than push someone into a procedure that produces a result they’ll need to manage again in two years.
Make the best investment in yourself and find out more about how we can help eliminate hair loss for good!
Hair Transplant Glasgow is centrally located and easily accessible from across Scotland. Find us in Glasgow City Centre:
Hair Transplant Glasgow
69 Buchanan Street
Glasgow
G1 3HL
Our Glasgow clinic is well connected by public transport:
If you are travelling by car, the clinic is a short drive from the M8 motorway with several car parks nearby, including the Buchanan Galleries multi-storey.
Most hairline transplants require between 1,200 and 2,500 grafts, depending on the degree of recession and the density you want to achieve. Early-stage recession (NW2) may need as few as 1,200–1,500 grafts. More significant recession into the temples typically requires 1,800 to 2,500 grafts. Your exact graft count is determined during consultation after Dr Elgindi has assessed your hairline and donor area.
Yes, when designed and performed correctly. The key to a natural looking hairline is the transition zone. We use single follicle grafts at the leading edge to replicate the softness of a real hairline, with micro-irregularity rather than a straight line. At our Glasgow clinic, hairline design is discussed and agreed with the patient before any surgery takes place.
A hairline procedure typically takes between 6 and 9 hours, depending on the number of grafts. The procedure is performed under local anaesthetic and most patients describe it as comfortable. You are awake throughout and can take breaks, eat, and use your phone during the session.
Transplanted hairs shed in the first few weeks , this is normal and expected. New growth begins at 3–4 months, with significant density visible from month 6. The full result, including maturation of the transplanted follicles, is assessed at 12 months. Most patients are happy with their hairline from around month 8–9 and experience continued improvement through to the 12-month mark.
Yes. Women are good candidates for a hairline hair transplant, and the two most common reasons for seeking one are a naturally high hairline they want to lower, or thinning at the temples caused by traction alopecia. Traction alopecia develops over time when hair is pulled tightly, typically through prolonged use of tight ponytails, braids, or extensions, and it most commonly damages the follicles at and around the temple area.
The shape of a woman’s hairline is more rounded than a man’s, which means there is more surface area to cover in order to create a result that looks naturally feminine. Because of this, women typically require more grafts than men for a hairline procedure. The average graft count for a female hairline transplant is around 2,000 to 2,300 grafts, though the exact number depends on the degree of raising or thinning being addressed and the density needed.
FUT is often a preferred option for women as it avoids shaving the donor area, so hair at the back of the scalp remains untouched throughout. Candidacy is assessed individually at your free consultation.
Transplanted follicles are taken from the permanent donor zone and are not subject to the DHT sensitivity that causes male pattern baldness. They will remain in place permanently. However, native hair behind the transplanted hairline can continue to thin if loss is progressive. This is why we plan for future loss during your consultation, designing a hairline that remains appropriate even if recession continues, and discussing medication options that may help stabilise native hair.
Aside from achieving fantastic results, we believe that keeping in touch with our patients before, during and after their hair transplantation procedure is paramount – it helps to keep our patients feeling calm and in control. We’re always on hand to provide guidance, support and aftercare advice. Time and again, our patients tell us that this is what sets us apart from other clinics.
You can read our great reviews of FUE hair transplants over on Google and Trustpilot



